

The 2027 E/M changes are taking shape, and coders should know what is final and what is still proposed. CMS released the CY 2027 Medicare Physician Fee Schedule (PFS) proposed rule on July 14, 2026. However, the final rule is not out yet, and CMS usually publishes it in early November. In this guide, we first review what CMS finalized for 2026. Then we walk through each 2027 proposal so you can plan, study, and code with confidence.
If you are new to this topic, start with our primer: What is Evaluation and Management (E/M) in Medical Coding.
Key Themes Behind E/M Coding Today
A few themes connect the 2026 and 2027 rules. For example, they help explain why CMS keeps adjusting E/M payment instead of the E/M codes themselves.
- Medical decision making (MDM) and time: Office visits are still leveled by MDM or total time. In addition, history and exam only need to be medically appropriate.
- Less checkbox documentation: The AMA reports that the E/M reforms have led to more clinically meaningful notes.
- Payment shifts through the fee schedule: CMS often changes how E/M is valued, so coders also need to watch conversion factors and practice expense.
- Rewarding longitudinal care: CMS continues to pay extra for ongoing, complex patient relationships through G2211.
What CMS Finalized for 2026
CMS issued the CY 2026 PFS final rule on October 31, 2025. Its policies took effect January 1, 2026. Because these rules are in force now, they are the baseline for every 2027 proposal.
| 2026 Final Policy | What It Does | Why It Matters for E/M |
|---|---|---|
| Two conversion factors | Qualifying APM participants get $33.57. Everyone else gets $33.40. | The same E/M code pays slightly more for clinicians in a qualifying Advanced APM. |
| Efficiency adjustment of 2.5% | CMS cut work RVUs and intraservice time by 2.5% for non-time-based services. | E/M is exempt. Likewise, care management, behavioral health, and telehealth list services are exempt. |
| Practice expense shift | Facility services now get 50% of the indirect practice expense per work RVU that office services get. | As a result, office E/M fares better than the same visit billed in a facility setting. |
| G2211 for home visits | CMS added G2211 to home or residence E/M codes 99341, 99342, 99344, 99345, 99347, 99348, 99349, and 99350. | Previously, G2211 applied only with office codes 99202 to 99205 and 99211 to 99215. |
2026 Telehealth and Supervision Rules
- Virtual direct supervision is permanent: Supervisors may be present through real-time audio and video. However, audio-only does not count, and 010 or 090 global services are excluded.
- Frequency limits are gone: CMS removed the limits on subsequent inpatient visits, subsequent nursing facility visits, and critical care consultations.
- CPT telemedicine codes 98000 to 98015: CMS again declined to add them to the Medicare Telehealth Services List. Instead, Medicare telehealth visits still use the regular E/M codes. Still, commercial payers may accept the CPT telemedicine codes.
- Behavioral health add-ons: In addition, CMS created G0568, G0569, and G0570 for use with Advanced Primary Care Management (APCM) in the same month.
The 2026 proposed rule also asked for comments on separate urgent care E/M coding. That idea was a request for input, so keep following CMS updates before you change urgent care coding.
2027 E/M Changes CMS Has Proposed
The items below come from the CY 2027 PFS proposed rule. None of them is final yet. Therefore, treat each one as a watch item until the final rule confirms it.
| 2027 Proposal | What CMS Proposed | What Coders Should Watch |
|---|---|---|
| Lower conversion factors | $33.17 for qualifying APM participants (down 1.19%) and $32.84 for everyone else (down 1.68%). | The cut happens mainly because the one-year 2.5% boost for 2026 expires. |
| G2211 becomes a modifier | A new modifier, called MOD1 for now, would add 16% to the E/M payment at every level. | So, instead of a separate add-on line, the modifier would go on the E/M code itself. |
| ACO modifier | A second modifier, MOD2, would add 32% for Shared Savings Program ACO or LEAD Model clinicians. | Its use is voluntary. Also, it could apply to all of the clinician’s Medicare patients. |
| Same-day E/M with a procedure | When a separately identifiable office E/M and a 0, 10, or 90 day global procedure happen on the same day, the higher valued service pays 100%. Meanwhile, the other service pays 50%. | This applies to the same physician or a physician in the same practice. As a result, modifier 25 visits could pay less. |
| Advance care planning | CPT 99497 and 99498 would count only the billing practitioner’s own time. Two new HCPCS codes would cover clinical staff ACP. | Notes would need to show who spent the time, because staff time would move to the new codes. |
Proposed RPM and RTM Changes
CMS also proposed tighter rules for remote monitoring, which often starts at an E/M visit.
- Remote therapeutic monitoring (RTM) would be limited to established patients.
- Before RPM or RTM begins, the practitioner would have to furnish a separately reportable initiating visit.
- Only clinical staff employed by the practice could furnish the services, not contractors.
- Finally, CMS asked for comments on bundling the RPM and RTM codes into four new HCPCS G codes.
Proposed Practice Expense and Telehealth Items
In addition, CMS proposed moving away from AMA survey data for practice expense over several years. It also asked whether the facility and non-facility payment difference still makes sense for hospital-employed physicians. For telehealth, the in-person requirement for mental health visits would not apply through December 31, 2027. Similarly, RHCs and FQHCs could bill non-behavioral telehealth visits through that date.
CPT 2027 Code Set
The AMA released the CPT 2027 code set on September 9, 2026, and it takes effect January 1, 2027. It includes 299 new codes, 74 revisions, and 80 deletions. However, the AMA announcement does not describe changes to the office E/M codes. Even so, always check the E/M section of your 2027 CPT book before you code.
What Did Not Change
- Office and outpatient E/M levels are still chosen by MDM or by total time on the date of the encounter.
- E/M stayed exempt from the 2026 efficiency adjustment because it is a time-based service.
- History and exam still need only to be medically appropriate, so checkbox reviews of systems do not raise the level.
Leveling Refresher: MDM or Time
Pick the method that best supports the visit. Then make the method clear in the note, for example “Level based on MDM” or “Total time 32 minutes.”
- MDM: Base the level on problems addressed, data reviewed or ordered, and the risk of patient management.
- Time: Count the total practitioner time on the date of service. This includes face-to-face and non-face-to-face work, such as reviewing records and documenting.
| New Patient | Minimum Time | Established Patient | Minimum Time |
|---|---|---|---|
| 99202 | 15 minutes | 99212 | 10 minutes |
| 99203 | 30 minutes | 99213 | 20 minutes |
| 99204 | 45 minutes | 99214 | 30 minutes |
| 99205 | 60 minutes | 99215 | 40 minutes |
Do not count clinical staff time. Also, leave out time spent on services you report separately.
Documentation Checklist for Your EHR Template
If coding by MDM:
- Problems: List each condition with its status, severity, and any differential diagnosis.
- Data: Note tests ordered or reviewed, external notes, an independent historian, independent interpretation, and discussion with another clinician.
- Risk: Record the options considered, prescription drug management, procedures, and social factors that limit care.
If coding by time:
- Add up all qualifying practitioner work on the date of service.
- Exclude staff time and separately billed services, such as ACP if it is reported on its own.
Practical Tips to Prepare for 2027
- Build a G2211 policy now. Write clear criteria for the longitudinal relationship. That way, you can switch smoothly if CMS finalizes the modifier.
- Review modifier 25 visits. Because the same-day proposal could cut one service to 50%, flag high-volume procedure clinics for revenue review.
- Separate ACP time. Ask providers to document their own ACP time apart from staff time.
- Check RPM and RTM workflows. Confirm that each patient has an initiating visit and that staff are employed by the practice.
- Update payer grids. Medicare and commercial payers differ on telemedicine codes, so keep a payer-by-payer list.
- Watch for the final rule. Finally, compare every item here with the CY 2027 final rule when CMS publishes it in November.
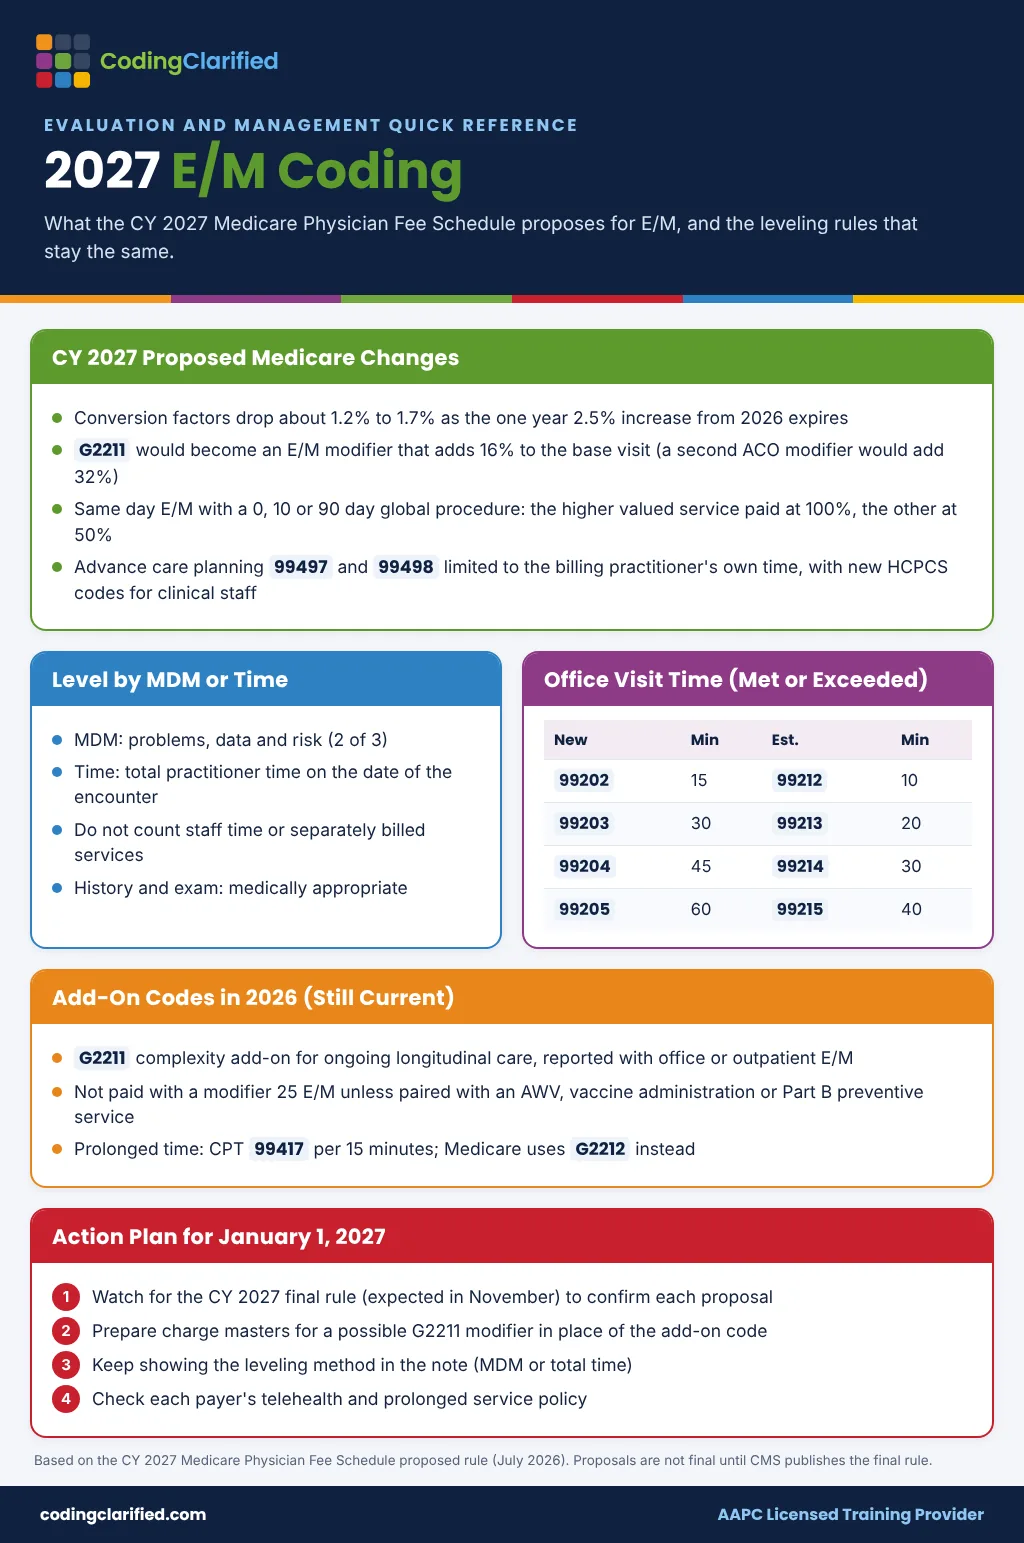
2027 E/M Quick Reference Cheat Sheet
Use this one-page summary as a study aid. However, confirm each proposed item against the final rule and your payer policies.
References
- American Medical Association: E/M changes have led to more clinically meaningful documentation
- CMS: CY 2026 PFS proposed rule fact sheet (efficiency adjustment and practice expense)
- CMS: CY 2026 PFS proposed rule fact sheet (G2211 and telehealth proposals)
- CMS: CY 2026 PFS proposed rule fact sheet (urgent care comment request)
- CMS: CY 2026 PFS final rule fact sheet (CMS-1832-F), October 31, 2025
- CMS: CY 2027 PFS proposed rule fact sheet, July 14, 2026
- American Medical Association: AMA releases CPT 2027 code set, September 9, 2026