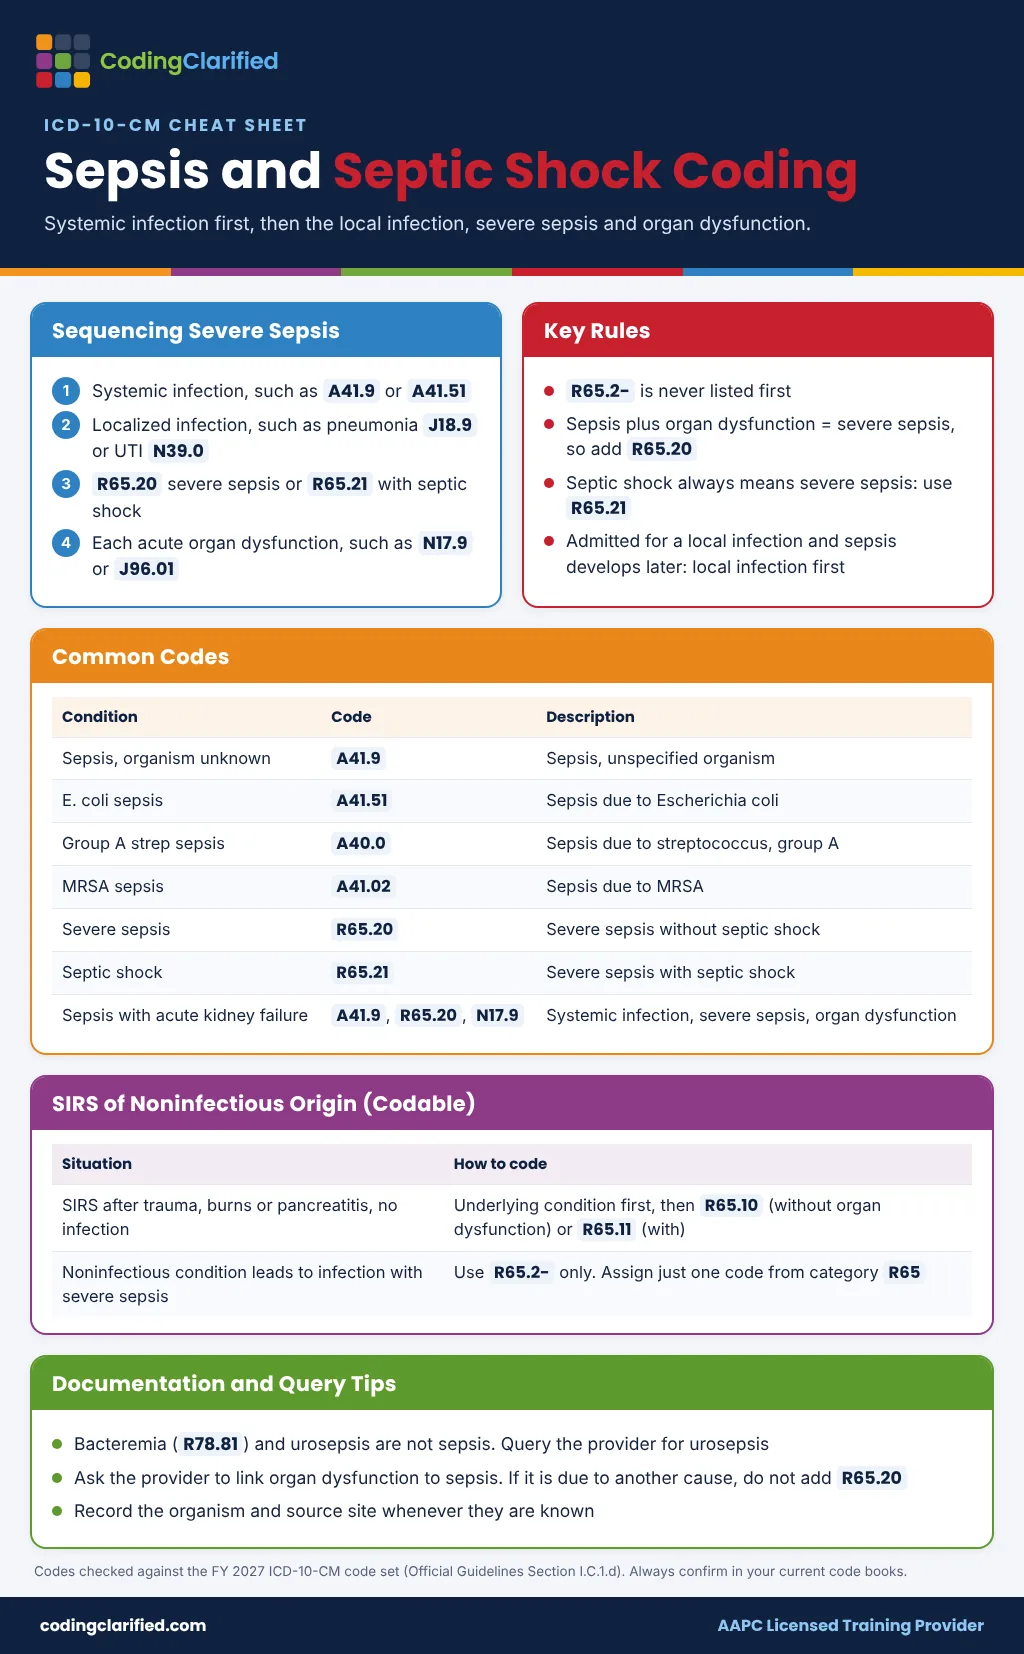
Guidelines and Tips for Billing and Medical Coding Sepsis & Septic Shock
Sepsis and septic shock are serious medical conditions that require prompt diagnosis and treatment. Proper coding and billing for sepsis and septic shock are crucial for accurate reimbursement and compliance with healthcare regulations. Medical coders must be meticulous when coding these conditions. These conditions have specific guidelines, and coders must follow them to ensure accurate claims submission.
In this blog, we’ll explore the guidelines for coding sepsis and septic shock. We will also cover common mistakes to avoid and helpful tips for accurate coding and billing.
Understanding Sepsis and Septic Shock
Before diving into coding and billing, it’s essential to understand what sepsis and septic shock are:
-
Sepsis: Sepsis is a life-threatening condition. It occurs when the body’s response to infection leads to widespread inflammation, tissue damage, and organ dysfunction. It can occur in response to infections such as pneumonia, urinary tract infections (UTIs), or abdominal infections.
-
Septic Shock: Septic shock is a severe form of sepsis that causes a significant drop in blood pressure. As a result, it leads to organ failure and an increased risk of death. It is a medical emergency that requires immediate intervention.
Sepsis and Septic Shock Coding Guidelines
Coding sepsis and septic shock requires an understanding of the International Classification of Diseases, 10th Revision, Clinical Modification (ICD-10-CM) codes. You also need to know how coders use them to describe these conditions accurately.
Sepsis Coding Guidelines:
Most sepsis codes in ICD-10-CM fall under A40–A41 and represent different types of infections that can lead to sepsis. The correct code depends on the infection site, the organism causing the infection, and the patient’s specific condition.
-
A40 – Streptococcal sepsis
-
A41 – Other sepsis (which includes a variety of causes such as Gram-negative organisms or sepsis of unknown origin)
So here are some key guidelines to follow:
-
Document the Causative Organism: When a specific pathogen causes sepsis, the provider must document the organism. For example, A40.0 (Group A streptococcal sepsis) or A41.51 (Sepsis due to Escherichia coli [E. coli]).
-
Sepsis Documentation: If a specific pathogen did not clearly cause the sepsis, use the appropriate A41.9 code (Sepsis, unspecified organism).
-
Sepsis is Often Accompanied by Organ Dysfunction: For sepsis with organ dysfunction (like renal failure, respiratory failure, etc.), sequence the systemic infection code first, such as A41.9. Then add R65.20 (severe sepsis without septic shock) or R65.21 (severe sepsis with septic shock). After that, add the organ dysfunction codes. For example, use a code from category N17 (acute kidney failure), such as N17.9. Or use a code from category J96 (respiratory failure), such as J96.01 for acute respiratory failure with hypoxia.
Septic Shock Coding Guidelines:
ICD-10-CM classifies septic shock separately. Therefore, it’s critical to use the correct code for billing purposes.
-
R65.21 – Severe sepsis with septic shock: Use this code whenever the provider documents septic shock, because septic shock always means severe sepsis. However, never report R65.21 first. Code the systemic infection first.
-
Severe Sepsis: Severe sepsis refers to sepsis with signs of organ dysfunction or inadequate perfusion. These signs include hypotension (low blood pressure), respiratory failure, renal failure, or liver dysfunction. For severe sepsis without septic shock, use R65.20. When septic shock is present, use R65.21 instead, along with codes for the specific organ dysfunctions.
-
Septic Shock and Organ Dysfunction: If specific organ failure accompanies septic shock, include codes for the organ dysfunction (e.g., a code from category N17, such as N17.9, for acute kidney failure). Sequence them after the infection code and R65.21.
Key Documentation Tips for Sepsis and Septic Shock Coding
Accurate coding starts with proper documentation. So here are some tips to ensure that providers document sepsis and septic shock thoroughly:
-
Clearly Indicate Sepsis and Septic Shock: The medical record should explicitly state that the patient has sepsis or septic shock. However, simply listing “infection” or “bacteremia” may not be sufficient. These terms do not necessarily imply sepsis or septic shock.
-
Identify the Source of Infection: Sepsis coding requires documenting the source of the infection. For example, the source may be a respiratory infection, urinary tract infection, or abdominal infection. Knowing the infection’s site also helps with accurate coding.
-
Note Organ Dysfunction: Sepsis often leads to organ dysfunction. If organ dysfunction is present (e.g., acute renal failure, respiratory failure, or cardiovascular collapse), the provider should document the specific dysfunctions. Then coders can assign the appropriate codes.
-
Document the Causative Organism: Whenever possible, document the pathogen or microorganism responsible for the infection, such as a specific bacterium or virus (e.g., A41.51 for Escherichia coli sepsis).
-
Include Severe Sepsis and Septic Shock Diagnosis: If the provider documents both severe sepsis and septic shock, code R65.21 (Severe sepsis with septic shock). Be sure to include all organ dysfunctions.
Common Mistakes in Sepsis and Septic Shock Coding
Sepsis and septic shock coding may seem straightforward. However, there are several common pitfalls to avoid:
-
Incorrect Use of Sepsis Codes: Never code septic shock alone. First, code the underlying systemic infection, such as A41.9 (Sepsis, unspecified organism) when the provider does not identify the organism. Then add R65.21 for septic shock.
-
Not Documenting Organ Dysfunction: Sepsis often causes organ dysfunction. As a result, failing to document the specific organ failure can lead to incomplete coding. Therefore, ensure that the provider properly documents all associated organ failures.
-
Misunderstanding of Severe Sepsis vs. Septic Shock: Severe sepsis refers to sepsis with organ dysfunction. In contrast, septic shock specifically involves a drop in blood pressure that leads to organ failure. It’s important to differentiate between these two when coding.
-
Failure to Report Underlying Infection: If a specific infection (e.g., pneumonia, UTI, etc.) causes the sepsis, the provider should document it clearly and the coder should code it appropriately. Do not simply code sepsis without documenting the underlying infection.
Sepsis and Septic Shock Billing Tips
Once you assign the proper codes, there are additional billing considerations to keep in mind:
-
Accurate Documentation: Ensure that all medical documentation supports the codes you are submitting. Inaccurate or incomplete documentation can lead to claim denials or audits.
-
Billing for Sepsis-Related Services: Sepsis and septic shock often require extensive treatment, including laboratory tests, imaging, and ICU care. Therefore, make sure the documentation and codes cover all services provided.
-
Modifiers: Use appropriate modifiers when necessary to indicate additional procedures or services during the treatment of sepsis and septic shock. For example, use modifier 25 for an E/M service performed on the same day as a procedure.
-
Preventive and Post-Discharge Care: Sepsis can have long-term health impacts. If the patient requires ongoing treatment or follow-up care after discharge, code and bill these services correctly.
Important Considerations for Sepsis and Septic Shock Billing
-
Payer Policies: Different payers may have specific guidelines for sepsis and septic shock billing. So always check the payer’s policies before submitting a claim.
-
Coding for Comorbidities: If the patient has comorbid conditions that complicate their sepsis (e.g., diabetes or immunocompromised state), confirm the provider documents them. Then code them appropriately as secondary diagnoses.
-
Complications of Sepsis: Sepsis can lead to complications such as acute respiratory distress syndrome (ARDS), disseminated intravascular coagulation (DIC), and multi-organ failure. Code these complications as secondary diagnoses.
Accurate coding and billing for sepsis and septic shock are critical for proper reimbursement and compliance with medical regulations. Therefore, coders should follow ICD-10-CM guidelines carefully and include all relevant documentation. They should also correctly identify the causative organism, organ dysfunctions, and other complicating factors. By following these guidelines and using the appropriate codes for sepsis and septic shock, healthcare providers can help ensure accurate claims submission and reduce the risk of audits or denials.
CMS CMS ICD-10-PCS guideline reference
Coding Clarified Blog Medical Coding Blog
Let Coding Clarified “clarify” coding for you!