
Quick answer: Medical decision making (MDM) is one of two ways to select an office or outpatient E/M level; the other is total time. Coders score MDM on three elements: the number and complexity of problems addressed, the amount and complexity of data reviewed and analyzed, and the risk of complications from patient management. You assign a level when two of the three elements meet or exceed it: straightforward (99202, 99212), low (99203, 99213), moderate (99204, 99214), or high (99205, 99215).
What Is Medical Decision Making (MDM) in E/M Coding?
It plays a significant role when you determine the appropriate level of service to report for a patient encounter. As of the 2021 updates (and continuing today), the American Medical Association (AMA) and Centers for Medicare & Medicaid Services (CMS) simplified the E/M coding guidelines for office and outpatient services. As a result, these guidelines now focus more on Medical coding MDM or time.
Here’s a detailed guide to Medical Decision Making (MDM) for coding and billing:
What Are the Three Elements of MDM?
Specifically, three elements determine MDM:
-
Number and Complexity of Problems Addressed
-
Amount and/or Complexity of Data to be Reviewed and Analyzed
-
Risk of Complications and/or Morbidity or Mortality of Patient Management
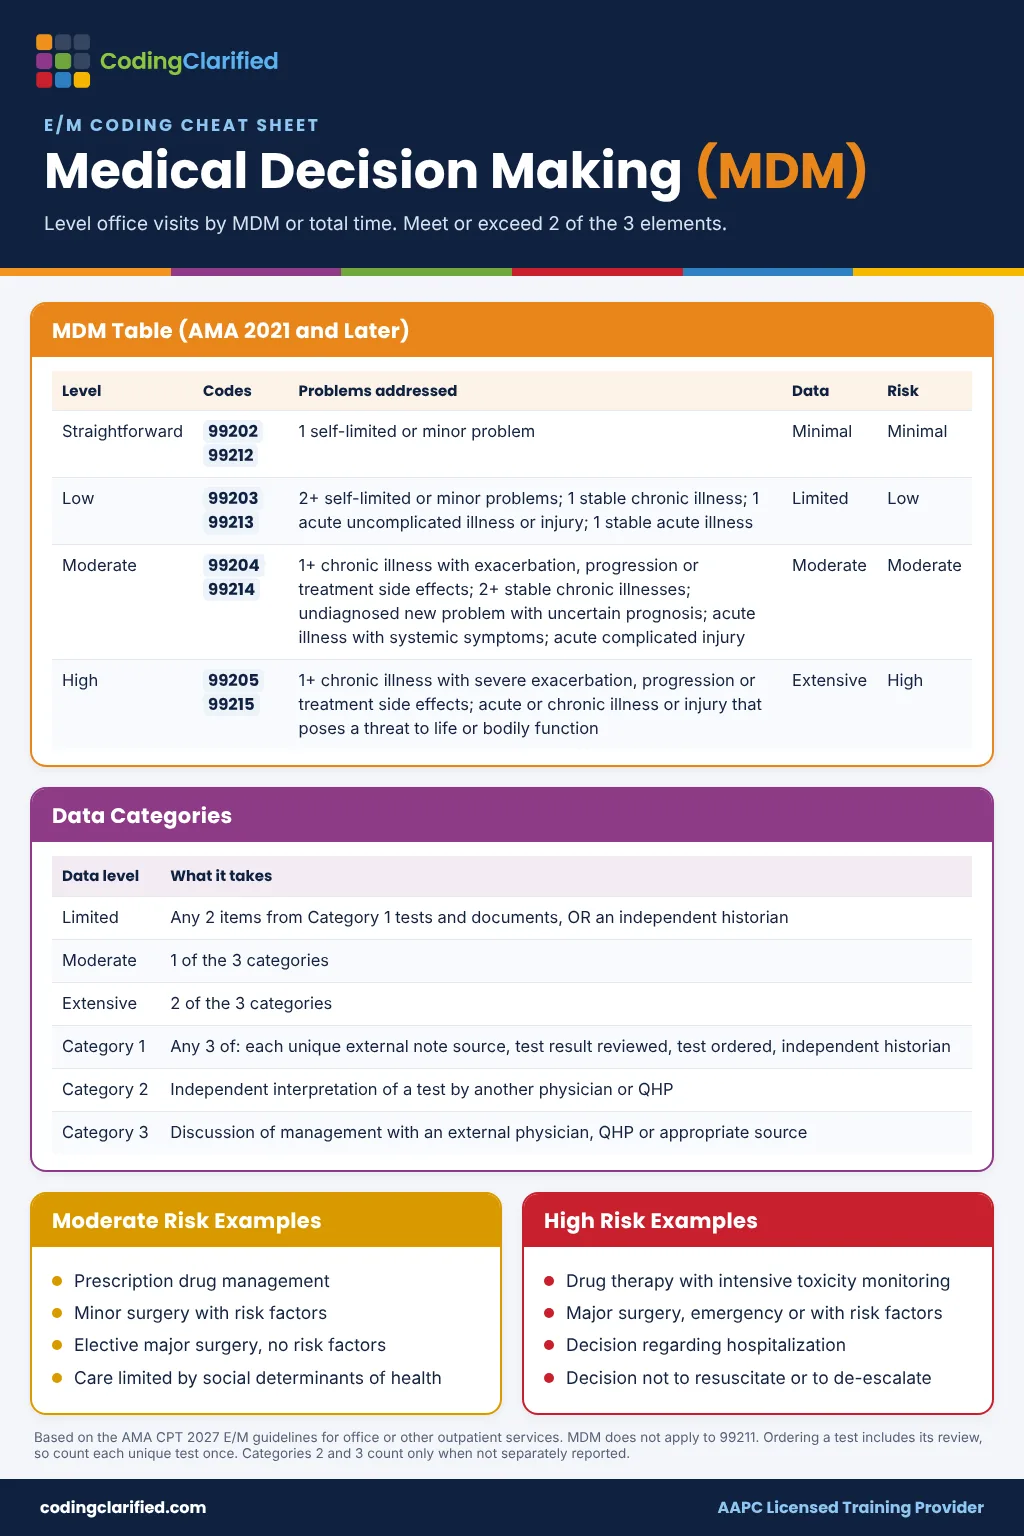
In short, you must meet or exceed two out of three elements to support a particular MDM level.
What Are the Four Levels of MDM?
There are four levels of MDM:
| MDM Level | Problems Addressed | Data Reviewed | Risk |
|---|---|---|---|
| Straightforward | 1 self-limited or minor problem | Minimal or none | Minimal risk of complications or morbidity |
| Low | 2+ self-limited/minor problems, or 1 stable chronic illness | Limited (e.g., 2 unique tests or documents, or an independent historian) | Low risk (e.g., OTC meds, minor procedures) |
| Moderate | 1+ chronic illness with exacerbation or 2+ stable chronic illnesses | Moderate (e.g., 3 tests or documents, an independent interpretation, or a discussion with an external physician) | Moderate (e.g., prescription drugs, minor surgery with risk) |
| High | 1+ chronic illnesses with severe exacerbation or acute illness posing threat to life/function | Extensive (e.g., at least two of the three data categories) | High (e.g., drug therapy requiring intensive monitoring for toxicity, decision to hospitalize) |
Element Details
Problems Addressed
A problem is “addressed” when it is actively evaluated, treated, or managed at the encounter.
-
Stable chronic illness is considered less complex than an exacerbated chronic illness or an acute problem with systemic symptoms.
Data Reviewed and Analyzed
Three types:
-
Category 1: Tests, documents, or independent historian (review of external notes, review of each unique test result, ordering of each unique test, or an assessment that requires an independent historian)
-
Category 2: Independent interpretation of a test performed by another physician or QHP (not separately reported)
-
Category 3: Discussion of management or test interpretation with an external physician, other QHP, or appropriate source (not separately reported)
- In addition, ordering a test includes its later review, so count each unique test only once.
Risk of Complications and/or Morbidity/Mortality
Specifically, risk includes:
-
Management decisions made (e.g., prescription, procedures)
- Management options considered, including options the patient declines
-
Nature of diagnostic/therapeutic interventions (e.g., elective surgery with identified risk factors)
How Do You Code MDM Accurately?
Document Clearly
-
-
Above all, avoid ambiguous language. Be specific: “acute exacerbation” is stronger than “symptoms today.”
-
Note decision-making rationale even if no new tests or treatment is ordered.
Support Risk Appropriately
-
If prescribing meds, justify risk level (e.g., “start on anticoagulant due to atrial fibrillation”).
-
If recommending follow-up only, explain why that’s medically appropriate.
-
-
Avoid Overcoding or Undercoding
-
-
Don’t automatically assign higher MDM due to comorbidities unless they are addressed during the encounter.
-
However, a thorough history and exam do not affect MDM level under 2021+ guidelines. Instead, MDM or time determines the code.
-
Use AMA MDM Grid
-
-
Use the official AMA grid for documentation as well as audit support.
-
This grid is available in the current CPT Professional Edition as well as on the AMA website.
-
What Do Auditors Look for in MDM Documentation?
-
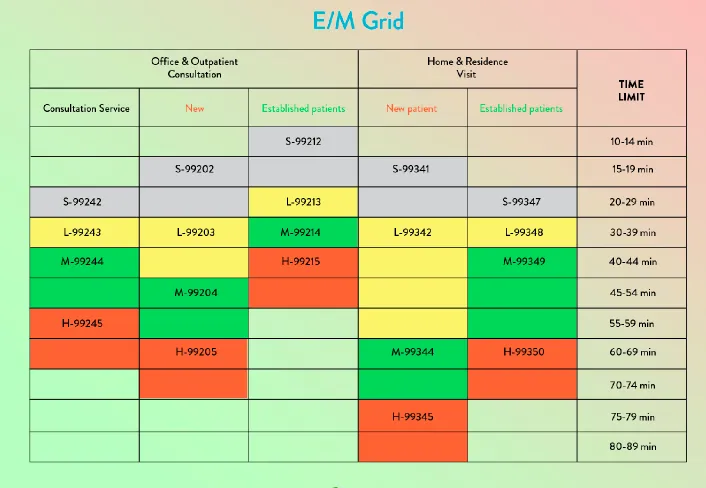
Time-based Coding (if used instead of MDM): Total time spent by provider on the date of service (face-to-face + non-face-to-face).
-
EHR Templates: Customize templates so they prompt detailed documentation of MDM elements.
-
Audit Trail: Keep documentation that reflects your decision-making, particularly for high-risk situations.
Resources for Further Reading
Coding Clarified E M 2025
AMA CPT E/M Guidelines (2025) AMA 2023 E/M descriptors and guidelines
CMS E/M Services Guide CMS E/M services guide
Interactive tools for E/M services
MDM Quick Reference for Office Visits
| MDM level | New patient | Established patient | Example of the risk element |
| Straightforward | 99202 | 99212 | Minimal risk, such as rest or a bandage |
| Low | 99203 | 99213 | Low risk, such as over-the-counter drugs |
| Moderate | 99204 | 99214 | Prescription drug management |
| High | 99205 | 99215 | Drug therapy requiring intensive monitoring for toxicity, or a decision about emergency major surgery or hospitalization |
Two of the three elements (problems, data and risk) must meet or exceed the level selected. Code 99211 does not require MDM.
A Note on G2211 and Modifier 25
When G2211 started in 2024, Medicare did not pay it on an office visit billed with modifier 25. Beginning in 2025, CMS allows G2211 with modifier 25 when the separately identifiable office visit is reported on the same day as an annual wellness visit, vaccine administration or a Medicare Part B preventive service. Read more in our G2211 guide.
Frequently Asked Questions About MDM
What are the three elements of MDM?
The number and complexity of problems addressed, the amount and complexity of data reviewed and analyzed, and the risk of complications, morbidity or mortality of patient management.
How many MDM elements must be met?
Two of the three.
Is prescription drug management moderate risk?
Yes. Prescription drug management is an example of moderate risk in the AMA MDM table.
Does history and exam still count toward MDM?
No. History and exam should be medically appropriate, but they do not determine the level for office visits.