Burn Coding Guidelines 2026: ICD-10-CM, CPT, Rule of Nines, TBSA & Debridement
Medical coding for burns requires more than choosing a diagnosis based on burn degree. Coders must identify the depth, anatomic location, laterality, total body surface area (TBSA), encounter type, cause, and treatment performed. In addition, multiple burns may require careful sequencing.
Burn coding becomes even more challenging when the patient has burns of different degrees, multiple body sites, chemical burns, smoke inhalation, infection, or extensive debridement.
This 2026 guide explains ICD-10-CM burn coding, CPT burn treatment codes, the Rule of Nines, TBSA coding, sequencing, debridement, and common mistakes that coders and CPC students should know.
Key Takeaways
- ICD-10-CM distinguishes thermal burns from chemical corrosions.
- Burns are generally classified by site and degree.
- When multiple burns are present, sequence the highest-degree burn first when appropriate under the burn sequencing guidelines.
- When different degrees occur at the same anatomic site and same side, report the highest degree documented for that site.
- Separate burn sites generally require separate ICD-10-CM codes.
- T31.- identifies the percentage of body surface involved by burns, while T32.- applies to corrosions.
- The Rule of Nines helps estimate TBSA.
- CPT burn treatment codes 16000, 16020, 16025, and 16030 depend on the type and extent of treatment.
- Documentation should clearly identify burn depth, location, laterality, TBSA, treatment, and encounter status.
- Never select a burn code based only on the word “burn.” Instead, verify all required details in the ICD-10-CM Tabular List.
For additional help with the coding process, review our guide to coding correctly with CPT, ICD-10-CM, and HCPCS.
What Coders Need to Know About Burns in 2026
The ICD-10-CM Official Guidelines distinguish burns from corrosions. Thermal burns may result from fire, hot objects, electricity, or radiation. Chemical burns, however, are classified as corrosions.
Current burns involving external body surfaces generally fall within categories T20-T25. Meanwhile, burns and corrosions of the eye and internal organs fall within T26-T28.
Burns are commonly described clinically as:
- First degree — superficial involvement with erythema
- Second degree — partial-thickness injury, often with blistering
- Third degree — full-thickness involvement
However, coders should always code from the provider’s documentation rather than interpreting clinical findings independently.
How to Code Burns in ICD-10-CM
A good burn-coding workflow starts with several questions.
First, where is the burn? Next, determine its documented degree and laterality. Then, identify the encounter type, extent, and external cause when applicable.
For example, a burn diagnosis may require details such as:
- Right versus left
- Hand versus forearm
- First, second, or third degree
- Initial, subsequent, or sequela encounter
- Percentage of TBSA involved
- Percentage involving third-degree burns
- Thermal versus chemical injury
Therefore, documentation specificity directly affects code specificity.
ICD-10-CM Burn Categories
Important burn and corrosion categories include:
- T20.- — Burn and corrosion of head, face, and neck
- T21.- — Burn and corrosion of trunk
- T22.- — Burn and corrosion of shoulder and upper limb, except wrist and hand
- T23.- — Burn and corrosion of wrist and hand
- T24.- — Burn and corrosion of hip and lower limb, except ankle and foot
- T25.- — Burn and corrosion of ankle and foot
- T26-T28 — Burns and corrosions involving the eye and internal organs
- T30.- — Burn and corrosion, body region unspecified
- T31.- — Burns classified according to extent of body surface involved
- T32.- — Corrosions classified according to extent of body surface involved
Because T30.- lacks site specificity, coders should use it rarely when documentation provides a more specific location.
How to Sequence Multiple Burns
When a patient has multiple burns, ICD-10-CM sequencing rules become especially important.
Generally, when the encounter is for treatment of multiple external burns, sequence the code reflecting the highest-degree burn first. Afterward, report additional burn sites as appropriate.
For example, suppose a patient has:
- Second-degree burn of the right forearm
- Third-degree burn of the left lower leg
The third-degree burn generally takes sequencing priority because it represents the highest degree.
However, principal diagnosis or first-listed diagnosis selection can change when the patient also has conditions such as smoke inhalation or respiratory failure. Therefore, coders must consider the circumstances of the admission or encounter rather than automatically assuming the external burn will always be first-listed.
Different Burn Degrees at the Same Site
This rule is frequently tested on certification exams.
When a patient has burns of different degrees involving the same anatomic site and same side, classify the burn to the subcategory representing the highest degree documented.
For instance, if the right thigh contains both second- and third-degree burns, the coder reports the third-degree burn classification for that site rather than separately coding both degrees.
Conversely, separate anatomic burn sites usually require separate codes.
CPC Student Tip
Remember:
Same site + different degrees = code the highest degree.
Different sites = code each documented site.
That simple distinction can help eliminate several wrong answers on CPC-style questions.
Rule of Nines and Total Body Surface Area
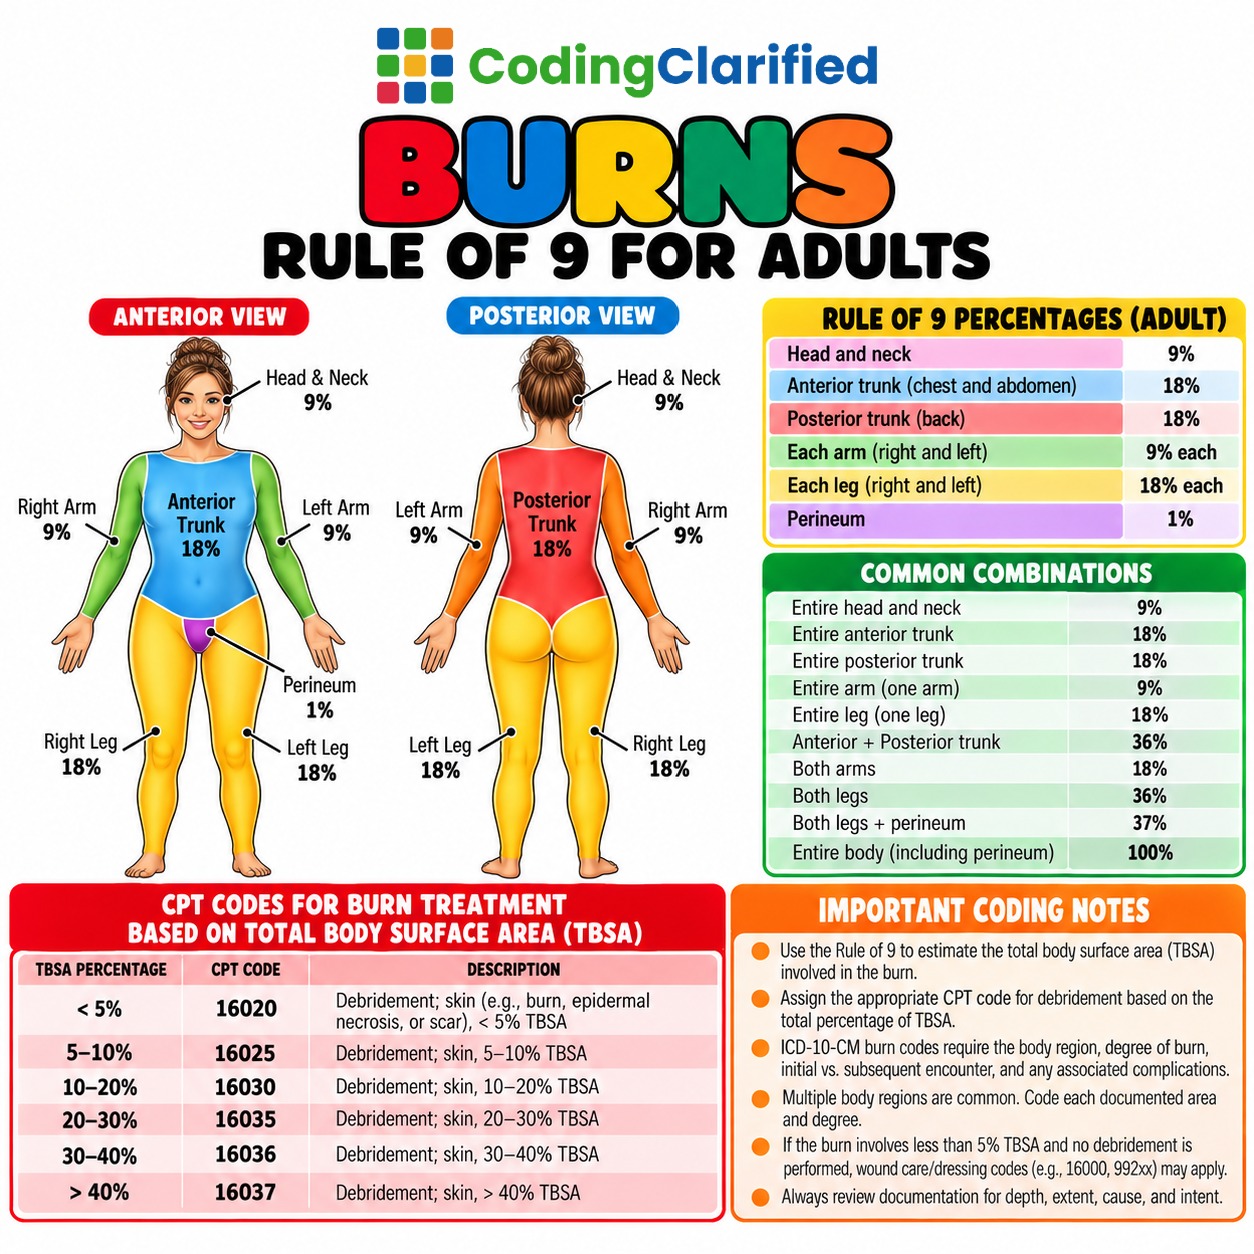
The Rule of Nines provides a quick method for estimating the percentage of an adult’s body affected by burns.
For adults, the traditional percentages are:
- Head and neck — 9%
- Each arm — 9%
- Anterior trunk — 18%
- Posterior trunk — 18%
- Each leg — 18%
- Genitalia/perineum — 1%
Together, these areas equal 100%.
However, body proportions differ in children. Therefore, clinicians may use adjusted percentages or the Lund and Browder chart when a more precise pediatric calculation is needed.
Coders should use the provider’s documented TBSA rather than independently calculating a diagnosis from a photograph or vague clinical description.
Using ICD-10-CM Category T31 for TBSA
Category T31.- classifies burns according to the percentage of total body surface involved.
For example, the code structure separates patients with burns involving progressively larger percentages of the body and may further identify the percentage involving third-degree burns.
These codes can provide important information for burn centers, severity reporting, and data analysis.
Importantly, T31.- may serve as an additional code when appropriate. ICD-10-CM also advises its use for reporting when a third-degree burn involves 20% or more of the body surface.
For chemical corrosions, use the corresponding T32.- category when appropriate.
Do not use T31.- or T32.- for burn or corrosion sequelae.
CPT Burn Treatment Codes for 2026
Diagnosis coding tells the payer what condition the patient has. CPT coding, in contrast, reports what the provider did.
Common CPT burn treatment codes include:
16000 — First-Degree Burn Treatment
CPT 16000 describes initial treatment of a first-degree burn when no more than local treatment is required.
For example, treatment might include cleansing, topical medication, cooling measures, or other documented local care.
Because 16000 describes initial treatment, coders should carefully distinguish it from codes used for partial-thickness burn care.
16020 — Small Partial-Thickness Burn
CPT 16020 describes dressing and/or debridement of partial-thickness burns when the treated area is less than 5% TBSA.
Therefore, documentation should support both the partial-thickness nature of the burn and its extent.
16025 — Medium Partial-Thickness Burn
CPT 16025 applies to dressing and/or debridement of a medium partial-thickness burn.
Examples include the whole face, a whole extremity, or approximately 5% to 10% TBSA.
16030 — Large Partial-Thickness Burn
CPT 16030 describes dressing and/or debridement of a large partial-thickness burn.
Generally, this includes more than one extremity or greater than 10% TBSA.
Because CPT code selection depends heavily on the documented size of the treated area, missing TBSA documentation can make accurate coding difficult.
For additional information about wound treatment, see our medical coding wound care guide.
Burn Debridement Coding
Debridement removes damaged, devitalized, contaminated, or necrotic tissue. However, coders should not assume every burn treatment supports a separate wound debridement code.
The documentation must clearly describe the service performed.
For burn-specific partial-thickness treatment, CPT 16020, 16025, and 16030 already describe dressing and/or debridement based on the size of the burn.
More extensive procedures may require different CPT coding. Therefore, always review the operative or procedure note and current CPT instructions before assigning a code.
Documentation should identify:
- Burn location
- Burn depth
- TBSA or treated area
- Tissue treated or removed
- Method of debridement
- Whether anesthesia was required
- Other separately performed procedures
Learn more in our medical coding debridement guide.
Non-Healing and Infected Burns
A non-healing burn does not automatically become an aftercare diagnosis.
Instead, ICD-10-CM instructs coders to code non-healing burns as acute burns. Necrosis of burned skin is likewise coded as a non-healed burn.
Additionally, when the provider documents infection of a burn site, assign an additional code identifying the infection.
Therefore, coders should review the complete record rather than replacing the burn diagnosis with an infection code.
Initial, Subsequent, and Sequela Encounters
Many burn codes require a seventh character.
The seventh character describes the phase of care rather than simply whether this is the patient’s first visit.
An initial encounter applies while the patient receives active treatment. Consequently, a patient may still qualify for an initial-encounter seventh character even when another provider treated the burn previously.
A subsequent encounter generally applies during routine healing or recovery. A sequela, meanwhile, represents a late effect that remains after the acute injury has resolved.
CPC Student Tip
Do not think:
“First visit = A.”
Instead, think:
“Active treatment = A.”
This distinction appears frequently in injury coding questions.
External Cause Coding for Burns
External cause codes can explain how and where an injury occurred.
Depending on documentation and reporting requirements, these codes may identify:
- Cause or mechanism
- Intent
- Place of occurrence
- Activity
- Work-related status
For example, a burn might result from hot liquid, fire, electricity, chemicals, or another documented source.
However, external cause reporting requirements can vary by payer, facility, and jurisdiction. Therefore, coders should follow applicable reporting rules rather than automatically assuming every claim requires every external cause code.
Can You Report an E/M Service With Burn Treatment?
Sometimes.
An E/M service may be separately reportable when the provider performs a significant and separately identifiable E/M service beyond the work normally associated with the procedure.
When documentation supports separate reporting, modifier 25 may be appropriate on the E/M service.
However, simply evaluating the patient enough to perform burn treatment does not automatically justify a separate E/M code.
Coders should review the documentation, CPT instructions, NCCI edits, and payer requirements before reporting both services.
Common Mistakes to Avoid When Coding Burns
Coding Every Degree at the Same Site
Do not separately report multiple burn degrees at the same anatomic site and same side. Instead, code the highest degree documented for that site.
Using an Unspecified Site Too Quickly
Avoid T30.- when the medical record identifies the actual body region. Specific documentation should lead to specific coding.
Confusing Burns and Corrosions
Thermal burns and chemical corrosions do not follow identical code paths. Therefore, identify the cause before finalizing the diagnosis code.
Forgetting TBSA
Large burns often require documentation of TBSA. Moreover, TBSA can affect both diagnosis reporting and CPT treatment selection.
Assuming First Visit Means Initial Encounter
The seventh character relates to the phase of treatment, not simply the chronological visit number.
Coding From the Index Without Checking the Tabular List
The Alphabetic Index helps locate the code. However, the Tabular List confirms required characters, laterality, instructions, and other details.
Automatically Billing a Separate E/M
A procedure does not automatically support an additional E/M service. Instead, documentation must demonstrate significant, separately identifiable evaluation and management work.
2026 Burn Coding Documentation Checklist
Before submitting a burn claim, verify that the medical record identifies:
- Burn versus chemical corrosion
- Exact anatomic site
- Laterality when applicable
- Burn degree or depth
- TBSA when relevant
- Percentage of third-degree involvement when applicable
- Active treatment versus healing versus sequela
- Cause of injury
- Infection or other complications
- Dressing, debridement, grafting, or other treatment performed
- Size or extent of the treated area
- Separate E/M work when reported
A consistent checklist can improve accuracy and reduce missed information.
For another real-world example, review our Burn Emergency Department Coding Case Study.
CPC Exam Tips for Burn Coding
Burn questions can look complicated because they often include several injuries, percentages, and treatment details. However, a step-by-step method makes them easier.
First, identify every burn location. Next, mark the degree beside each site. Then, determine which burn represents the highest degree.
Afterward, check laterality, TBSA, and the encounter seventh character. Finally, verify your answer in the Tabular List and apply sequencing rules.
For CPT questions, switch your focus from the diagnosis to the actual procedure. Determine whether the provider treated a first-degree burn or performed dressing/debridement for a partial-thickness burn. Then, identify the size or TBSA category.
Most importantly, do not let extra clinical details distract you from what the question asks.
2026 Coding Update: FY 2026 vs. FY 2027 ICD-10-CM
Because ICD-10-CM updates follow the federal fiscal year, coders working during calendar year 2026 may use two different fiscal-year code sets.
The FY 2026 ICD-10-CM guidelines apply through September 30, 2026. Beginning October 1, 2026, coders should use the FY 2027 ICD-10-CM code set and guidelines for applicable dates of service.
Therefore, always verify the patient’s date of service before selecting the code set.
For official guidance, coders should review the CMS ICD-10 resources and the AAPC coding resources. CPT code selection should also be verified against the current AMA CPT code set and applicable payer policies.
Frequently Asked Questions About Burn Coding
What ICD-10-CM codes are used for burns?
Current external burns generally fall within T20-T25, depending on the body site. Burns and corrosions of the eye and internal organs fall within T26-T28, while T31.- and T32.- classify the extent of body surface involved in burns and corrosions, respectively.
Do you code first- and second-degree burns at the same site separately?
No. When different degrees of burns occur at the same anatomic site and on the same side, code the highest degree documented for that site. Therefore, a second-degree burn generally represents that site when first- and second-degree burns occur together there.
What is the Rule of Nines in burn coding?
The Rule of Nines estimates the percentage of total body surface affected by burns. In adults, the head and neck equal 9%, each arm 9%, each leg 18%, the anterior trunk 18%, posterior trunk 18%, and genitalia 1%. However, pediatric proportions differ.
What is the difference between T31 and T32?
Category T31.- reports burns according to the extent of body surface involved. Category T32.-, in contrast, reports corrosions according to the extent of body surface involved.
Which CPT code is used for a small partial-thickness burn?
CPT 16020 describes dressing and/or debridement of a small partial-thickness burn involving less than 5% TBSA. However, coders should always verify the current CPT descriptor and documentation before reporting the service.
Which CPT code is used for a partial-thickness burn over 10% TBSA?
CPT 16030 describes dressing and/or debridement of a large partial-thickness burn, such as a burn involving more than one extremity or greater than 10% TBSA. Again, documentation must support the size and treatment performed.
Are non-healing burns coded as acute burns?
Yes. ICD-10-CM guidelines instruct coders to classify non-healing burns as acute burns. Additionally, necrosis of burned skin is coded as a non-healed burn.
Can a separate E/M service be billed with burn treatment?
Yes, when the documentation supports a significant and separately identifiable E/M service beyond the work included in the burn procedure. In those situations, modifier 25 may be appropriate. Nevertheless, coders should verify CPT, NCCI, and payer-specific requirements before submitting both services.
Coding Clarified Final Thoughts
Burn coding requires coders to connect the clinical documentation with several different coding concepts. Specifically, accurate claims depend on identifying burn depth, site, laterality, TBSA, encounter type, cause, and treatment.
Moreover, ICD-10-CM sequencing rules matter when multiple burns are present. CPT selection, meanwhile, depends on exactly what the provider performed and, for common partial-thickness burn treatment codes, the size of the area treated.
As 2026 progresses, remember the October 1 transition from FY 2026 to FY 2027 ICD-10-CM. Finally, always verify codes against the current ICD-10-CM Tabular List, CPT manual, official coding guidelines, NCCI edits, and payer policies before submitting a claim.