

Mastering Medical Coding and Risk Adjustment: Tips for the AAPC CRC Exam
Medical coding in the realm of risk adjustment plays a crucial role in healthcare finance and patient care management. As you prepare for the AAPC Certified Risk Adjustment Coder (CRC) exam, here are essential tips to help you excel:
What Is the CRC Certification?
The Certified Risk Adjustment Coder (CRC) is AAPC’s credential for risk adjustment coding. It shows employers you can review medical records and capture every supported diagnosis that affects a patient’s risk score, accurately and compliantly. I work in HCC coding every day, and it is one of the best second credentials a coder can earn.
What Risk Adjustment Coding Involves
Medicare Advantage and other value based plans receive payment based on how sick their members are. Risk adjustment coders read the full record, find chronic and serious conditions the provider documented and treated, and assign ICD-10-CM codes that map to Hierarchical Condition Categories (HCCs). The documentation must support every captured code, because RADV audits recover payment for codes it does not support.
HCC Coding Basics
- Diagnosis codes drive the score. Risk adjustment uses ICD-10-CM, not CPT.
- Providers must document conditions every year. If the provider does not address a chronic condition in a face to face encounter during the year, it does not count.
- Support matters. The provider must show that they monitored, evaluated, assessed, or treated the condition.
- Hierarchies apply. When related conditions fall in the same family, only the most severe one counts.
Who Hires CRC Coders?
Medicare Advantage plans, provider groups, risk adjustment vendors, and auditing firms all hire CRC coders, and much of the work is remote once you have experience. For example, roles include HCC coder, risk adjustment coder, chart reviewer, and RADV auditor.
Does the CRC Pay More?
Specialty credentials generally pay more than the CPC alone, and risk adjustment is one of the most requested specialties in coding job postings. However, pay depends on your experience, accuracy, productivity, and whether you move into auditing or quality roles. For a full breakdown, see our medical coding salary guide.
CRC Exam Format and Cost
| Exam detail | CRC |
|---|---|
| Questions | 100 multiple choice |
| Time | 4 hours in one sitting, proctored |
| Passing score | 70% |
| Price | $499, which includes two attempts |
| Allowed book | One approved ICD-10-CM code book |
| To maintain | Active AAPC membership and 36 CEUs every two years |
AAPC sets and changes these details, so confirm them on the AAPC CRC page before you buy.
CPC First, Then CRC
Most coders earn the CPC first because it covers all three code sets and matches most entry level jobs. The CRC is a natural next step, and our students get a head start: the Coding Clarified HCC internship puts you on real risk adjustment charts after you pass the CPC. See every option in our medical coding certifications guide.
CRC Exam Tips
BREAKDOWN OF THE 100-QUESTION CRC EXAM
Passing the CRC exam requires you to correctly answer a minimum of 70 questions from the domains below.
The exam will rely on a level of understanding that enables you to identify the domain.
Compliance (15 questions)
These questions will assess your knowledge of the process for prospective audits, RADV audits, and retrospective audits, and your ability to identify common coding errors identified in RADV audits.
Protecting our programs’ sustainability for future generations by serving as a responsible steward of public funds is a CMS Strategic pillar. The Medicare Advantage Risk Adjustment Data Validation (RADV) program is CMS’ primary way to address improper overpayments to Medicare Advantage Organizations (MAOs). During a RADV audit, CMS confirms that the enrollee’s medical record supports any diagnoses an MAO submitted for risk adjustment.
RADV audits occur after the final risk adjustment data submission deadline for the MA contract year and after CMS recalculates the risk factors for affected individuals to determine if payment adjustments are necessary.
A risk adjustment discrepancy occurs when an enrollee’s HCCs used for payment differ from the HCCs that CMS assigns. The HCCs used for payment come from MAO self-reported data. In contrast, CMS assigns its HCCs from the medical record review it performs through the RADV audit process. Aggregating risk adjustment discrepancies can determine an overall level of payment error.
Diagnosis Coding Domain
These questions will assess your ability to apply Coding Clinic guidance to coding scenarios and identify common coding errors in risk adjustment as well as the diagnosis codes that risk adjust.
- Amputations Z89 Acquired absence of limb
- Artificial openings Z93 Artificial opening status
- Atherosclerosis I70.90 Unspecified atherosclerosis
- AV fistulas I77.0 Arteriovenous fistula, acquired
- CHF I50 Heart failure
- CKD N18 Chronic kidney disease (stage)
- Complications of devices T85.6 Mechanical complication of other specified internal and external prosthetic devices, implants and grafts
- COPD J44.9 Chronic obstructive pulmonary disease, unspecified
- CVA/Stroke I63 Cerebral infarction
- Dementia F03.9 Unspecified dementia, unspecified severityDepression F32 Depressive episodeDiabetes E08 Diabetes mellitus due to underlying condition E09 Drug or chemical induced diabetes mellitus E10 Type 1 diabetes mellitus E11 Type 2 diabetes mellitus E13
- Other specified diabetes mellitus
- DVT I82.40 Acute embolism and thrombosis of unspecified deep veins of lower extremityHIV/AIDS B20 Human immunodeficiency virus disease
- Hypertension I10 Essential (primary) hypertension
- Malnutrition E46 Unspecified protein-calorie malnutrition
- Manifestations of diseases (e.g., DM, stroke, COPD)
- Mental disorders F99 Mental disorder, not otherwise specified
- Neoplasms C00-D49 code range for neoplasms Use Neoplasm Table in the ICD-10
- Pneumonia J18.9 Pneumonia, unspecified organism
- Pressure ulcers L89.90 Pressure ulcer of unspecified site unspecified stagePulmonary embolism I26 Pulmonary embolism
- Pulmonary fibrosis J84.10 Pulmonary fibrosis, unspecified
- Seizures G40.89 Other seizures
- Skin ulcers L98.499 Non-pressure chronic ulcer of skin of other sites with unspecified severity
Documentation Improvement Domain
This section will test your knowledge of communicating documentation discrepancies with providers and your ability to identify documentation discrepancies.
Coding Errors
Unbundling codes
Unbundling involves submitting multiple codes for the different parts of a procedure that belong under a single code. As a result, this can artificially inflate the reimbursement amount, and payers generally do not allow it.
Overcoding/Undercoding
Overcoding occurs when a healthcare provider submits a code suggesting a more severe illness or procedure than the provider genuinely carried out.
Undercoding occurs when a provider employs a code that doesn’t aptly capture the intricacy or intensity of the services rendered, resulting in lower reimbursements.
Inaccurate Coding
With the extensive collection of ICD-10 codes numbering over 78,000 and the frequent incorporation of new codes by CMS, it has become increasingly imperative for both seasoned and novice coders to undergo ongoing training to maintain their current proficiency.
Neglecting NCCI Edits for Multiple Codes
NCCI edits are sets of rules that identify code pairs or groups that the same provider typically should not bill together for the same patient on the same day.
Duplicate Billing
When a provider bills the same medical service or procedure more than once for a single patient during the same visit or treatment period.
When a provider bills the same medical service or procedure more than once for a single patient during the same visit or treatment period.
Inappropriate Modifier Application with Inadequate Documentation
Please see the Coding Clarified CPT modifier blog.
Improper Code Usage
- Incorrect procedure code
Using the wrong procedure code based on incomplete medical records can lead a provider to perform the wrong procedure. As a result, this could be risky for the patient.
- Incorrect diagnosis
Entering the wrong diagnosis can be risky for the patient.
Using Unlisted Codes without Proper Documentation
Coders typically use unlisted codes when no specific existing code precisely represents the provided service.
Anatomy and Quality of Care Domains
This section will assess your ability to identify common acronyms for industry and medical terminology and identify anatomic structures, locations, and functions. The exam also asks you to define common medical terms and explain disease processes and interactions for common chronic conditions.
This area will test your ability to explain the purpose of HEDIS and STAR ratings, as well as their alignment with risk adjustment.
Risk Adjustment Model Domains
This section will ask that you explain the use of data mining and Predictive modeling from data captured through risk adjustment coding. You must also demonstrate the ability to apply trumping in the risk adjustment hierarchy.
HCC Risk Adjustment Models
This section will assess your ability to apply the ACA, CDPS, HCC, and private payer risk adjustment models. The exam also asks you to list the elements needed to determine the risk adjustment score.
CMS-HCC and HHS-HCC Models
-
CMS-HCC modelThe Centers for Medicare and Medicaid Services (CMS) created this model in 2004. CMS designed it to help predict medical costs for patients over 65 with complex healthcare needs.
-
HHS-HCC model
Created by the U.S. Department of Health and Human Services (HHS), this model uses a similar scoring mechanism and category structure as the CMS-HCC model. However, it applies to the general population. It primarily applies to commercial payers of the Affordable Care Act (ACA).
Coding Clarified Blog Abstracting from the EHR:
Medical Record Abstraction in 2026: How to Abstract EHR Documentation for Accurate Medical
Understanding the Basics of Risk Adjustment
Risk adjustment is a method health insurers use to compensate health plans that enroll a higher proportion of sicker members. This involves assigning diagnostic codes to patients based on their health conditions, which directly impacts reimbursement rates.
Key Knowledge Areas for the CRC Exam
- ICD-10-CM Coding: Proficiency in assigning accurate ICD-10-CM codes to reflect patient diagnoses is fundamental. Focus on understanding the guidelines for coding various conditions and diseases.
The most common chronic diagnosis conditions for HCCs currently listed by CMS: currently listed by CMS:
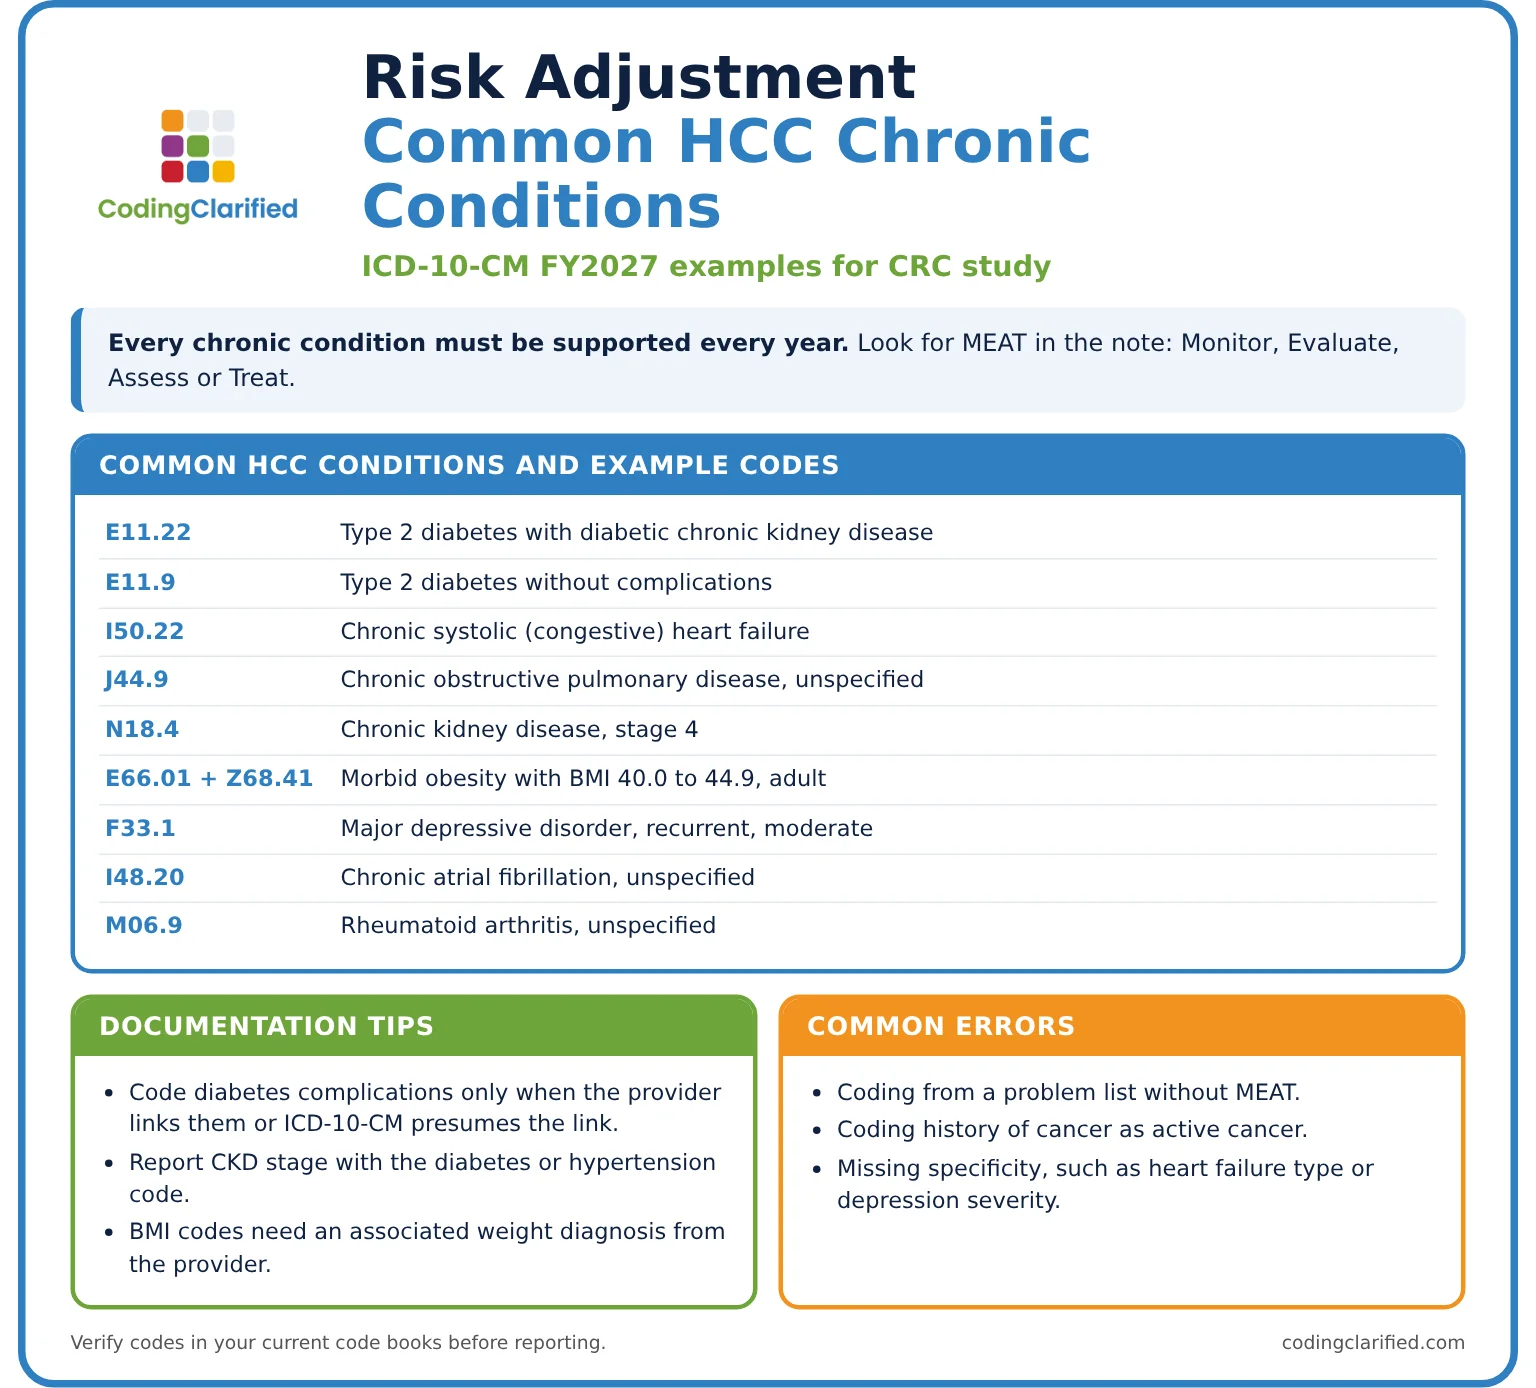 Source: Chronic Conditions | CMS
The most frequently missed ICD-10 codes:
- Artificial opening status – tracheostomy (Z93.0 HCC 82), gastrostomy (Z93.1 HCC 188), ileostomy (Z93.2 HCC 188), colostomy (Z93.3 HCC 188), cystostomy (Z93.50 HCC 188), urinary tract (Z93.6 HCC 188)
- Dependence on renal dialysis (Z99.2 HCC 134), Dependence on a respirator (ventilator) status (Z99.11 HCC 82)
- Long-term (current) use of insulin (Z79.4 HCC 19)
- Amputation Status Codes – Acquired absence toe(s), foot, ankle (Z89.411 – Z89.449 HCC 189)
- Functional quadriplegia – Complete immobility due to severe physical disability or frailty (R53.2 HCC 70)
HCC Coding Essentials
HCC Coding: Risk adjustment uses Hierarchical Condition Categories (HCCs) to categorize patients based on their diagnoses. Familiarize yourself with the HCC model and how it impacts reimbursement.
Some HCC codes that are more confusing than others, have a necessity for another ICD-10-CM diagnosis code connection or need detailed specificity.
Here are some examples:
- Body mass index (BMI) 40 or greater, adult (Z68.41-Z68.45 HCC 22): According to the Official Coding Guidelines for ICD-10-CM I.B.14, the BMI may be documented by other clinicians involved in the care of the patient (e.g. dietitian); however, the associated weight diagnosis (such as obesity or morbid obesity) must be documented by the provider. Many times, the record lists the BMI, but there is no documentation of obesity or morbid obesity. Both diagnoses are essential for appropriate code and HCC assignments. For instance, if the patient’s BMI of 40.5 is documented, no code is assigned and, therefore, no HCC. However, if the diagnosis of morbid obesity (E66.01) is also documented, along with the BMI 40.5 (Z68.41), then both codes can be accurately assigned resulting in an HCC 22 (morbid obesity), an additional relative risk factor of 0.250.
- COMA Scale (R40.2110 – R40.2444 HCC 80): According to the Official Coding Guidelines for ICD-10-CM I.C.18.e, the coma scale codes (R40.21- to R40.24-) can be used in conjunction with traumatic brain injury codes. They are primarily used by trauma registries, but they may be used in any setting where this information is collected. The Coma Scale codes should be sequenced after the diagnosis code(s). Like the BMI documentation, the Coma Scale may be documented by other clinicians, but the associated diagnosis (traumatic brain injury) must be documented by the provider. Some, but not all, of the Coma Scale codes equate to HCC 80.
Diabetes and Stroke Examples
- Diabetes HCCs 17, 18, 19: Diagnosis specificity documented by the provider is essential for correct HCC code assignments. One of the most common diagnoses documented is “Diabetes,” which coders assign to code E11.9 (Type 2 diabetes without complications). It equates to HCC 19 with a RAF score of 0.105. In comparison, if the provider documents Type 2 diabetes mellitus with hyperosmolarity (E11.00-E11.01) or Type 2 diabetes mellitus with ketoacidosis (E11.10-E11.11), both of which equates to HCC 17 RAF score 0.302. In contrast, if the documentation by the provider states Type 2 diabetes mellitus with diabetic nephropathy E11.21 or Type 2 diabetes mellitus with diabetic cataract E11.36, both of which equate to HCC 18 RAF score 0.302.
- History of Cerebral Infarction vs Cerebral Infarction with residual deficits: The documentation details surrounding a “history of stroke” is essential in correct code assignments. ICD-10-CM diagnosis code Z86.73 describes Personal history of transient ischemic attack (TIA), and cerebral infarction without residual deficits, which is an important code assignment for capturing the patient’s clinical history. However, it does not lead to an HCC. However, if the provider documents that the patient does have some residual deficits from a stroke, then the coder can assign an ICD-10-CM diagnosis code from category I69, Sequela of cerebrovascular disease. That code could also map to an HCC. For example, ICD-10-CM diagnosis code I69.051 (Hemiplegia and hemiparesis following nontraumatic subarachnoid hemorrhage affecting the right dominant side) equates to HCC 103 RAF score 0.437.
Chronic Kidney Disease Example
- Chronic Kidney Disease (CKD): As previously stated, documentation specificity is key to correct code and HCC assignment. And for CKD, the documentation of the CKD stage is essential. For example, CKD Stage 4 (N18.4 HCC 137 RAF 0.289) versus CKD unspecified (N18.9 no HCC). Also, CKD many times occurs alongside hypertension or diabetes. In these cases, the Official Coding Guidelines for ICD-10-CM guide additional ICD-10-CM codes as well as sequencing. For comparison, CKD Stage 5 due to Type 2 diabetes mellitus with diabetic chronic kidney disease would result in the following code assignments: (E11.22 HCC18 RAF 0.302) and (N18.5 HCC 136 RAF 0.289). YES HIM Consulting HCC coding cheat sheet
Guidelines, Anatomy, and the HCC Model
Documentation and Coding Guidelines: Ensure you know the official guidelines for both ICD-10-CM and HCC coding. Pay attention to specificity, sequencing, and documentation requirements.
CMS FY 2025 ICD-10-CM Official Guidelines
Anatomy and Physiology: A solid understanding of human anatomy and physiology is crucial for accurate coding. Therefore, prepare to apply this knowledge to clinical scenarios in the exam.
HCC Model:
Tips for Effective Preparation
- Study Resources: First, use AAPC’s CRC study guide and other recommended resources to build your knowledge base. In addition, AAPC Practice exams are particularly valuable for assessing your readiness.
- Hands-on Experience: If possible, seek practical experience in a healthcare setting that deals with risk adjustment coding. After all, real-world exposure enhances understanding and retention.
- Stay Updated: Keep abreast of changes in ICD-10-CM codes and guidelines. Also, subscribe to newsletters and attend webinars to stay informed about industry updates.
Exam Strategy
- Time Management: Pace yourself during the exam. Then allocate time based on the number of questions and sections. Also, flag challenging questions for review
-
Reading the question first
-
Scanning the case for keywords
-
Eliminating two answers
-
Read the guidelines
-
Highlight the guidelines
-
Take notes
-
Look for keywords
-
Check the first character of the code
-
Run straight to the answers
-
Look at the heading
-
Look for “with or with outs”:
-
Look for “do not report”
-
Check sequencing. Is a secondary code listed as a primary code? If so, eliminate this answer.
-
Can
-
Read notes under the codes. You can often eliminate answers based on note details.
-
Is a code mentioned in two answers? If so, go directly to that code to see if it fits the op notes and eliminate two answers based on what you find.
You can also apply many of the tips for the AAPC CPC exam to the AAPC CRC exam:
Tips to Pass the AAPC CPC Exam
Good Luck!
CRC Certification FAQs
How much does the CRC exam cost?
$499, which includes two attempts. You also need an active AAPC membership.
How many questions are on the CRC exam?
100 multiple choice questions in 4 hours. You need 70% to pass.
Can I take the CRC without the CPC?
Yes, but most coders earn the CPC first because it opens more entry level jobs. The CRC then adds a risk adjustment specialty.
What books can I use on the CRC exam?
One approved ICD-10-CM code book. AAPC does not allow other code books or references.
Is risk adjustment coding remote?
Much of it is, especially once you have experience. Many health plans and vendors hire remote HCC coders.